




The Disease
Typhoid fever and paratyphoid fevers: rare in metropolitan France
Typhoid fever and paratyphoid fevers are systemic salmonella infections that originate in the digestive tract. Typhoid fever is caused by the bacterium Salmonella enterica serotype Typhi. Paratyphoid fevers A, B, and C are caused, respectively, by Salmonella enterica serotypes Paratyphi A, Paratyphi B, and Paratyphi C.
Salmonella Paratyphi B comprises two types:
- the Java type (known as “d-tartrate positive”), which is a minor salmonella strain most commonly responsible for febrile gastroenteritis;
- the non-Java type (known as “d-tartrate-negative”), which causes paratyphoid fever B.
The reservoir for Salmonella Typhi and Paratyphi is strictly human (except for certain strains of Salmonella Paratyphi B, which can be found in both humans and animals).
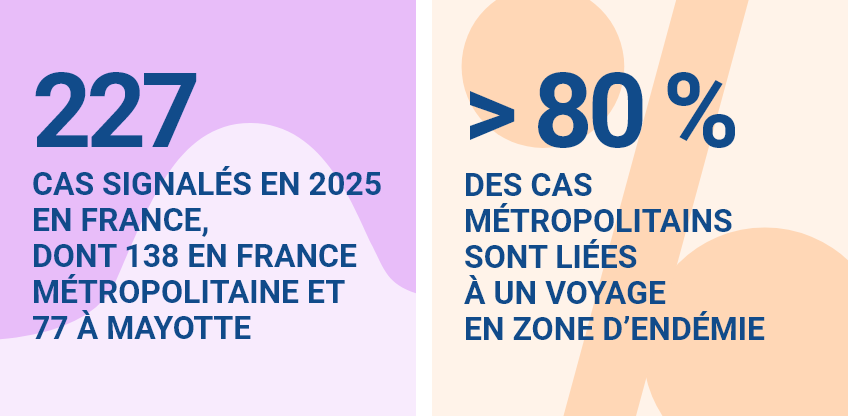
Typhoid fever and paratyphoid fevers are found worldwide. They are endemic in developing countries with poor sanitation (Asia, Africa, South America) and are rare and mostly sporadic in metropolitan France, where most cases are imported following a stay in an endemic area. In contrast, typhoid fever is endemic in Mayotte and French Guiana, with occasional outbreaks.
In 2020, the reduction in travel due to the global COVID-19 pandemic had a significant impact on the number of imported cases of typhoid and paratyphoid fever.
Key Statistics on Typhoid Fever and Paratyphoid Fevers
Transmission via feces
The source of contamination is the feces of people who are sick or who are asymptomatic carriers but excrete Salmonella Typhi or Paratyphi. Transmission is possible as long as the bacteria continue to be shed in the stool, typically starting in the first week of the illness and continuing throughout the recovery period.
For typhoid fever, approximately 10% of untreated patients continue to shed the bacteria for 3 months after the onset of symptoms, and 2 to 5% become chronic carriers with persistent Salmonella Typhi in the gallbladder.
Transmission is known as fecal-oral, either direct—through ingestion of bacteria from the stool of infected individuals (failure to wash hands, contaminated doorknobs, etc.), or—more commonly—indirectly through the ingestion of water or raw foods (seafood, vegetables, etc.) contaminated by the feces of infected individuals (sewage, manure spreading, etc.).
Prevention of infection relies on good personal and food hygiene, including avoiding the consumption—particularly when traveling in endemic areas—of unchecked water and raw or poorly washed foods. Typhoid fever and paratyphoid fevers are “dirty-hands diseases,” and the chain of transmission can be broken by thoroughly washing hands after contact with feces and before handling food.
Vaccination for Travelers
Two typhoid vaccines are currently available in France: an injectable vaccine and an oral vaccine in capsule form. These vaccines are currently recommended by the HCSP for travelers planning an extended stay (more than one month) or a stay under poor conditions in countries where hygiene standards are low and the disease is endemic. The injectable vaccine can be administered starting at age 2 and consists of a single injection to be given at least 15 days before departure. Protection lasts for 2 to 3 years. The oral vaccine can be administered starting at age 5 and consists of 3 capsules taken on Day 1, Day 3, and Day 5, with the first capsule to be taken at least 15 days before departure. Protection lasts for 3 years. Note, however, that these vaccines do not protect against paratyphoid fever: they should not replace precautionary measures regarding water and food, nor handwashing, which remain essential for preventing infection.
Varied Symptoms
The incubation period (the time between infection and the onset of the first symptoms) is most often 7 to 14 days but can range from 3 days to 1 month, depending on the individual and the amount of bacteria ingested.
Typhoid and paratyphoid fevers typically present with prolonged fever, headaches, anorexia (loss of appetite), splenomegaly (enlarged spleen), a rash on the trunk or abdomen, drowsiness (or even confusion), diarrhea, or—more commonly in adults—constipation. The clinical presentation may also be atypical, mild, or even asymptomatic, especially among people living in endemic areas. Paratyphoid fevers generally have a less severe clinical presentation than typhoid fever. Without treatment, complications may arise in about 10% of cases, involving the digestive tract (bleeding, perforations), heart, lungs, or nervous system. The case-fatality rate can reach 10% without treatment. In France, it is approximately 1 per 1,000 with appropriate antibiotic therapy.
The diagnosis is based on the isolation of the causative bacterium (Salmonella Typhi, Salmonella Paratyphi A, B, or C), most commonly in the blood, urine, or stool.
Serology (Widal test) to detect antibodies against Salmonella Typhi has little diagnostic value and should not be performed.
Antibiotic Treatment for Typhoid and Paratyphoid Fevers
Management of typhoid or paratyphoid fever may require hospitalization.
Treatment relies on antibiotics and must be adapted to account for possible bacterial resistance to antibiotics.
Reference materials
Circular of February 10, 2003, regarding the new system for anonymous reporting of notifiable infectious diseases. Weekly Epidemiological Bulletin 2003; 12-13:69-76
In relation to

Vaccination
thematic dossier
Contagious diseases most often affect children at a very young age. Because children are particularly vulnerable, they are a priority target for vaccination programs.











